
Explore Related Spine Guides
These articles form part of our comprehensive spine education series:
Neck
Lower back
Scoliosis & deformity
Mid back, tailbone & bone health
Refer a patient
Start here. How to refer, and what Dr Lau needs from you.
Conditions treated by Dr Lau
What we see, grouped by patient age.
About Dr Lau
For clinicians checking training and scope of practice.
By
Dr LAU Leok Lim
| Orthopaedic Surgeon (Spine Surgery), Singapore
Published: 3 September 2025 | Last reviewed: 2 September 2026
Degenerative Disc Disease (DDD) is one of the most common causes of neck and lower back pain. This guide explains how discs age, how degeneration is graded on MRI, and what treatment options are available in Singapore.
These articles form part of our comprehensive spine education series:
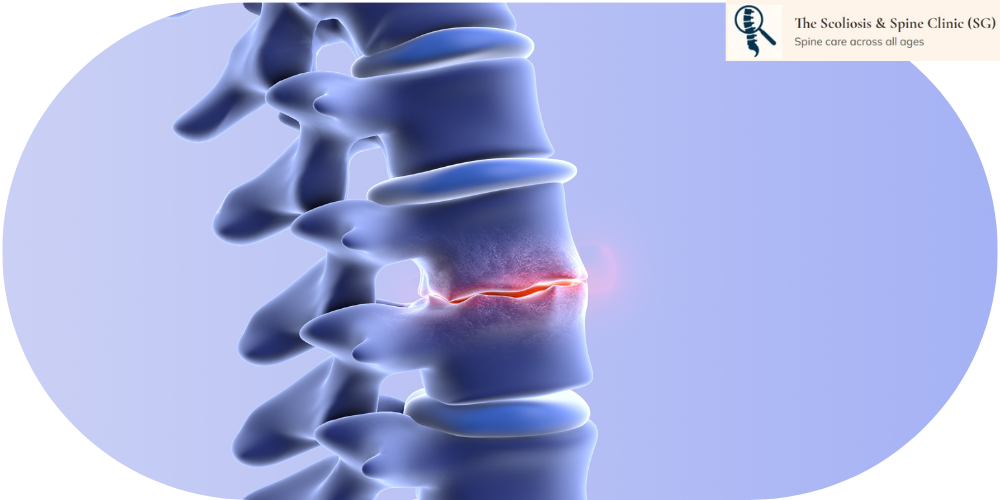
Degenerative Disc Disease – Age‑related disc dehydration and height loss
Degenerative Disc Disease (DDD) is a misnomer. It is not a disease, but a natural age‑related process where the intervertebral discs gradually lose hydration, height, and structural integrity. The spinal disc is often considered the weak link of the spinal column because it is the first structure to show signs of ageing.
Each disc functions as a shock absorber, allowing the spine to bend, twist, and carry load. Unlike most tissues in the body, the disc has no direct blood supply. Instead, it receives nutrients through diffusion across the vertebral endplates. As this diffusion becomes less efficient with age, the disc progressively dehydrates and degenerates.
Sometimes, patients experience a sudden worsening of symptoms — known as an exacerbation of DDD. This does not mean the disc suddenly “aged overnight.” Instead, it usually happens when a recent event places extra pressure on an already weakened disc. Examples include lifting something heavy, a sudden twist, prolonged sitting, or even a minor slip.
Disc degeneration follows a predictable pattern. Mild thoracolumbar disc degeneration can already be seen in individuals in their 20s. As people enter their 40s and beyond, the process accelerates, with more pronounced disc dehydration and disc height narrowing.
The L4/L5 level is most commonly affected due to its high mechanical load and mobility. The degree of disc height loss correlates strongly with the severity of disc degeneration. Radiologists describe this progression with the Pfirrmann scale, explained in Section 6 together with an interactive 3D model that plays through grades I to V.
When a radiologist writes "Pfirrmann grade 3" on your lumbar MRI report, they are using the most widely adopted scale for disc degeneration, described by Pfirrmann and colleagues in 2001. It reads the T2-weighted (fluid-sensitive) image and grades each disc from I, a healthy and well-hydrated disc, to V, a collapsed disc with no signal left. Four features are scored: how uniform the disc looks, whether the soft nucleus can still be told apart from the tougher outer annulus, how bright the disc is, and its height.
The model below opens on a healthy lumbar spine and plays the L4/L5 disc through grades I to V on its own: the disc darkens and loses height, the bone rims respond with osteophytes, and the facet joints and ligamentum flavum thicken until the space for the nerves narrows. When it finishes, take over: drag to rotate, set any grade on any level, and read the disc height, canal and foramen measurements as they change.
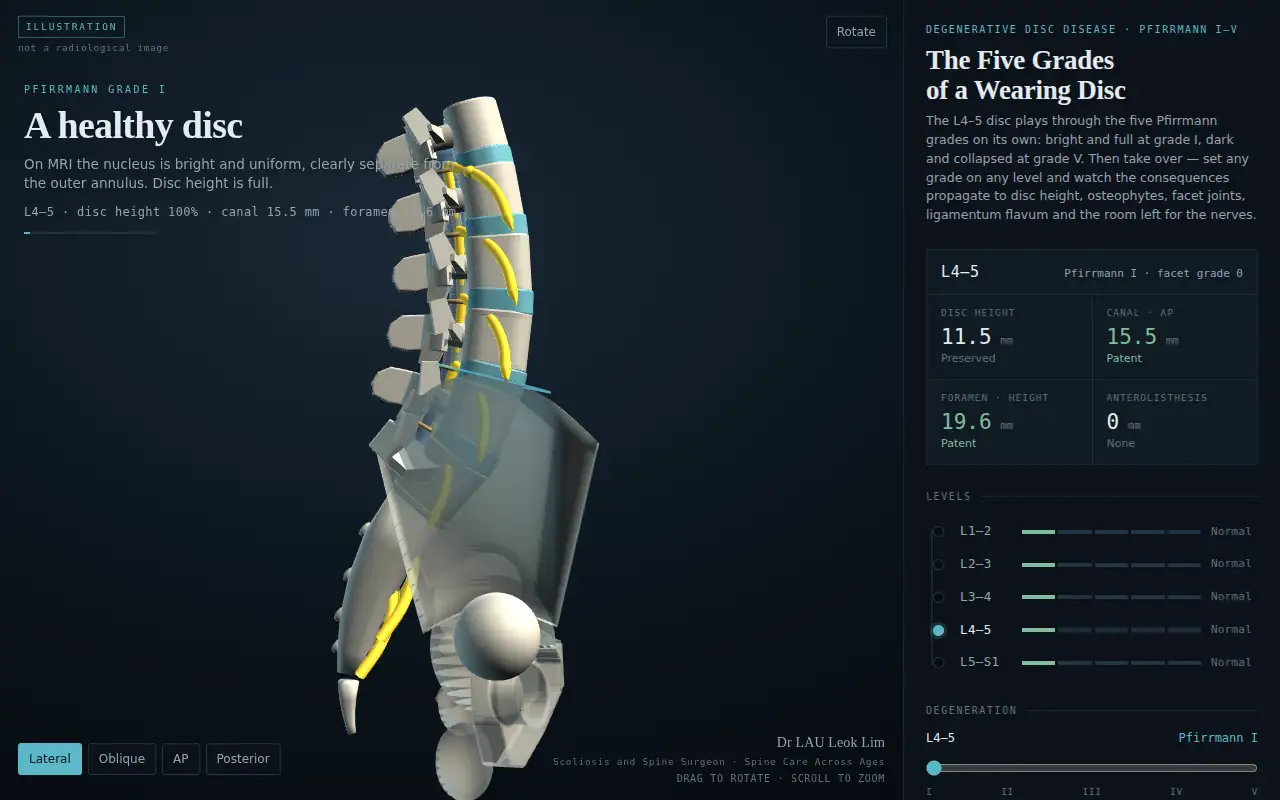
Loading the interactive model…
Open the model full-screen · Press ↻ Replay grades I–V inside the model to watch it again.
Educational illustration only. The anatomy is generated, not reconstructed from any patient's scan, and the measurements are representative. It does not replace clinical assessment or your own MRI.
| Grade | What the disc looks like on T2 MRI | Nucleus vs annulus | Signal (brightness) | Disc height |
|---|---|---|---|---|
| I | Uniform, bright white: a healthy, well-hydrated disc | Clearly separate | Bright, like fluid | Normal |
| II | No longer uniform; faint horizontal grey bands may appear | Clearly separate | Bright | Normal |
| III | Grey and patchy as water content falls | Boundary blurred | Intermediate | Normal or slightly reduced |
| IV | Dark grey to black; the disc begins to bulge and osteophytes form at the rims | Lost | Intermediate to dark | Normal to moderately reduced |
| V | Black, with a collapsed disc space; facets and ligamentum flavum take the load and thicken | Lost | Dark, no signal | Collapsed |
Reference: Pfirrmann CW, Metzdorf A, Zanetti M, Hodler J, Boos N. Magnetic resonance classification of lumbar intervertebral disc degeneration. Spine. 2001;26(17):1873–1878. doi:10.1097/00007632-200109010-00011
Degenerative Disc Disease – Educational Video
1. Is degenerative disc disease reversible?
No. Disc degeneration cannot be reversed, but symptoms can be effectively managed with targeted treatment.
2. Does disc degeneration always cause pain?
Not necessarily. Many people have disc degeneration on MRI without symptoms.
3. Can exercise help?
Yes. Core strengthening, flexibility training, and posture correction can reduce pain and improve function.
4. When should I see a spine specialist?
If pain persists beyond 6–8 weeks, radiates to the limbs, or affects daily activities, a specialist evaluation is recommended.
5. Does disc degeneration always lead to surgery?
No. Most patients improve with non‑surgical treatment. Surgery is reserved for severe nerve compression or instability.
6. My MRI report says Pfirrmann grade III or IV. Is that serious?
Usually not on its own. Grades III and IV are common findings in adults over 40 and describe a drier, darker disc, not the amount of pain you have. What matters is whether the disc has lost enough height to narrow the space for a nerve, and whether your symptoms and examination match. See Section 6 for what each grade means and a 3D model of the progression.